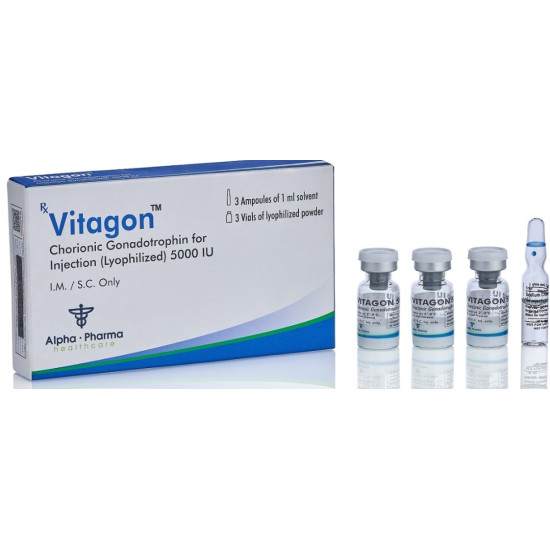
Vitagon 5000iu
(HCG) is not an anabolic/androgenic steroid but a natural protein hormone which
develops in the placenta of a pregnant woman. HCG is formed in the placenta
immediately after nidation. It has luteinizing characteristics since it is
quite similar to the luteinizing hormone LH in the anterior pituitary gland.
During the first 6-8 weeks of a pregnancy the formed HCG allows for continued
production of estrogens and gestagens in the yellow bodies (corpi luteum).
Later on, the placenta itself produces these 2 hormones.
HCG is manufactured from the urine of pregnant
women since it is exereted in unchanged form from the blood via the woman's
urine, passing through the kidneys. The commercially available HCG is sold as a
dry substance and can be used both in men and women. In women injectable HCG
allows for owlation since it influences the last stages of the development of
the ovum, thus stimulating ovulation. It also helps produce estrogens and
yellow bodies. The fact that exogenous HCG has characteristics almost identical
to those of the luteinizing hormone (LH) which, as mentioned, is produced in
the hypophysis, makes HCG so very interesting for athletes. In a man the
luteinizing hormone stimulates the Leydig's cells in the testes; this in turn
stimulates production of androgenic hormones (testosterone). For this reason
athletes use injectable HCG to increase the testosterone production.
Vitagon 5000iu (HCG) is often used in combination
with anabolic/androgenic steroids during or after treatment. As mentioned, oral
and injectable steroids cause a negative feedback after a certain level and
duration of usage. A signal is sent to the hypothalamohypophysial testicular
axis since the steroids give the hypothalamus an incorrect signal. The
hypothalamus, in turn, signals the hypophysis to reduce or stop the production
of FSH (follicle stimulating hormone) and of LH. Thus, the testosterone
production decreases since the testosterone-producing Leydig's cells in the
testes, due to decreased LH, are no longer sufficiently stimulated. Since the
body usually needs a certain amount of time to get its testosterone production
going again, the athlete, after discontinuing steroid compounds, experiences a
difficult transition phase which often goes hand in hand with a considerable
loss in both strength and muscle mass. Administering HCG directly after steroid
treatment helps to reduce this condition because HCG increases the testosterone
production in the testes very quickly and reliably. In the event of testicular
atrophy caused by megadoses and very long periods of usage, HCG also helps to
quickly bring the testes back to their original condition (size). Since
occasional injections of HCG during steroid intake can avoid a testicular
atrophy, many athletes use HCG for two to three weeks in the middle of their
steroid treatment. It is often observed that during this time the athlete makes
his best progress with respect to gains in both strength and muscle mass. The
reasons for this is clear. On the one hand, by taking HCG the athlete's own
testosterone level immediately jumps up and, on the other hand, a large
concentration of anabolic substances in the blood is induced by the steroids.
Many bodybuilders, powerlifters, and weightlifters report a lower sex drive at
the end of a difficult workout cycle, immediately before or after a
competition, and especially toward the end of a steroid treatment. Athletes who
have often taken steroids in the past usually accept this fact since they know
that it is a temporary condition. Those, however who are on the juice all year
round, who might suffer psychological consequences or who would perhaps risk
the breakup of a relationship because of this should consider this drawback
when taking HCG in regular intervals. A reduced libido and spermatogenesis due
to steroids in most cases, can be successfully cured by treatment with HCG.
Most athletes, however, use Vitagon 5000iu (HCG)
at the end of a treatment in order to avoid a "crash," that is, to
achieve the best possible transition into "natural training." A
precondition, however, is that the steroid intake or dosage be reduced slowly
and evenly before taking HCG. Although HCG causes a quick and significant
increase of the endogenic plasmatestosterone level, unfortunately it is not a
perfect remedy to prevent the loss of strength and mass at the end of a steroid
treatment. The athlete will only experience a delayed re-adjustment, as has
often been observed. Although HCG does stimulate endogenous testosterone
production, it does not help in reestablishing the normal
hypothalamic/pituitary testicular axis. The hypothalamus and pituitary are
still in a refractory state after prolonged steroid usage, and remain this way
while HCG is being used, because the endogenous testosterone produced as a
result of the exogenous HCG represses the endogenous LH production. Once the
HCG is discontinued, the athlete must still go through a re-adjustment period.
This is merely delayed by the HCG use. For this reason experienced athletes
often take Clomid and Clenbuterol following HCG intake or they immediately
begin another steroid treatment. Some take HCG merely to get off the
"steroids" for at least two to three weeks.
Many bodybuilders, unfortunately, are still of the
opinion that HCG helps them become harder while preparing for a competion by
breaking down subcutaneous fat so that indentations and vascularity are better
exposed. The HCG package insert states clearly that HCG has no known effect of
fat mobilization, appetite or sense of hunger, or body fat distribution. HCG
has not been demonstrated to be effective adjunctive therapy in the treatment
of obesity, it does not increase fat losses beyond that resulting from caloric
restriction.
Athlete should inject 5000 IU every 5 days. Since
the testosterone level, as explained, remains considerably elevated for several
days, it is unnecessary to inject HCG more than once every 5 days. The relative
dose is at the discretion of the athlete and should be determined based on the
duration of his previous steroid intake and on the strength of the various
steroid compounds. Athletes who take steroids for more than three months and
athletes who use primarily the highly androgenic steroids such as Androlic,
Sustanon 250, Cypionate, Dianabol (D-bol) etc. should take a relatively high
dosage. The effective dosage for athletes is usually 2000-5000 IU per injection
and should, as already mentioned, be injected every 5 days. HCG should only be
taken for a 4 weeks maximum.
If HCG is taken by male athletes over many weeks
and in high dosages, it is possible that the testes will respond poorly to a
later HCG intake and a release of the body's own LH. This could result in a
permanent inadequate gonadal function. Cycles on the HCG should be kept down to
around 3 weeks at a time with an off cycle of at least a month in between. For
example, one might use the HCG for 2 or 3 weeks in the middle of a cycle, and
for 2 or 3 weeks at the end of a cycle. It has been speculated that the
prolonged use of HCG could permanently, repress the body's own production of
gonadotropins. This is why short cycles are the best way to go.
Vitagon 5000iu (HCG) can in part cause side
effects similar to those of injectable testosterone. A higher testosterone
production also goes hand in hand with an elevated estrogen level which could
result in gynecomastia. This could manifest itself in a temporary growth of
breasts or reinforce already existing breast growth in men. Farsighted athletes
thus combine HCG with an antiestrogen. Male athletes also report more frequent
erections and an increased sexual desire. In high doses it can cause acne
vulgaris and the storing of minerals and water. The last point must especially
be observed since the water retention which is possible through the use of HCG
could give the muscle system a puffy and watery appearance. Athletes who have
already increased their endogenous testosterone level by taking Clomid and
intend subsequently to take HCG could experience considerable water retention
and distinct feminization symptoms (gynecomastia, tendency toward fat deposits
on the hips). This is due to the fact that high testosterone leads to a high
conversion rate to estrogens. In very young athletes HCG, like anabolic
steroids, can cause an early stunting of growth since it prematurely closes the
epiphysial growth plates. Mood swings and high blood pressure can also be
attributed to the intake of HCG. Vitagon 5000iu (HCG) is also suitable as
"over bridge" doping before a competition with doping controls.
HCG's form of administration is also unusual. The
substance choriongonadotropin is a white powdery freeze-dried substance which
is usually used as a compress. Based on the low structural stability of this
compress it can easily fall apart, thus giving the impression of a reduced
volume. This is, however, insignificant since there is neither a loss in effect
nor a loss of substance. Each package, for each HCG ampule, includes another
ampule with an injection solution containing isotonic sodium chloride. This
liquid, after both ampules have been opened in a sterile manner, is injected
into the HCG ampule and mixed with the dried substance. The solution is then
ready for use and should be injected intramuscularly. If only part of the
substance is injected the residual solution should be stored in the
refrigerator. It is not necessary to store the unmixed HCG in the refrigerator;
however, it should be kept out of light and below a temperature of 25°C. HCG is
a relatively expensive compound.
NandroRapid (Nandrolone Phenyl-prop) by Alpha-Pharma Healthcare is very
fast acting and therefore makes it possible for the compound to be out of the..